Is AI Really a Magic Wand in Emergency Departments?

Let’s paint a picture: In the bustling emergency department (ED), where every second counts, AI tools promise to sharpen doctors’ decision-making. But what if they don’t live up to what was promised? If that happens, how should we rethink the role of advanced tech when the stakes are high?
Background
Diagnostic errors are a persistent challenge for healthcare systems worldwide, affecting approximately 5–15% of patients [1, 2]. These errors are associated with higher mortality rates and represent one of the most common and costly sources of medical malpractice claims [3, 4]. This makes improving diagnosis not only a clinical goal but also a form of “source governance” that impacts medical costs, risk control, and overall patient well-being.
With the rapid advancement of digital health, Computerized Diagnostic Decision Support Systems (CDDSS) have emerged as a promising solution [5]. These AI-powered tools are designed to analyze symptoms and suggest differential diagnoses, with the goal of reducing errors, speeding up accurate diagnosis, and optimizing patient care [1, 6, 7]. Doctors can input patient health data into a CDDSS, which then generates a list of possible diagnoses and provides diagnostic recommendations. However, although such AI tools have shown acceptable performance in retrospective “vignette” studies, their real-world clinical effectiveness remains uncertain [1]. There is also a notable lack of high-quality prospective trial evidence to robustly support their widespread implementation.
Advances in machine learning, have accelerated the adoption of AI-based diagnostic support systems in EDs [1]. Yet the ED is a chaotic and emergency scenario, which is often overcrowded, understaffed, and faced with high-stakes decisions. Every second can shape life or death; misdiagnosis can lead to readmissions, escalated care, and soaring costs. Can promising study results truly translate into real-world impact in the setting of EDs?
New Evidence That Breaks the Mold
The question now has an answer from a recent study published in The Lancet Digital Health. To determine whether CDDSS truly improves outcomes in a real emergency setting, Hautz et al. conducted a multicenter, multiphase RCT across four Swiss emergency departments.
The trial involved 1,204 adult patients (18+) presenting with abdominal pain, unexplained fever, syncope, or non-specific symptoms. It compared outcomes between patients diagnosed with CDDSS support and those receiving standard care. The key finding is that using the CDDSS failed to reduce the rate of diagnostic quality risks compared to traditional diagnostic processes.
Implications
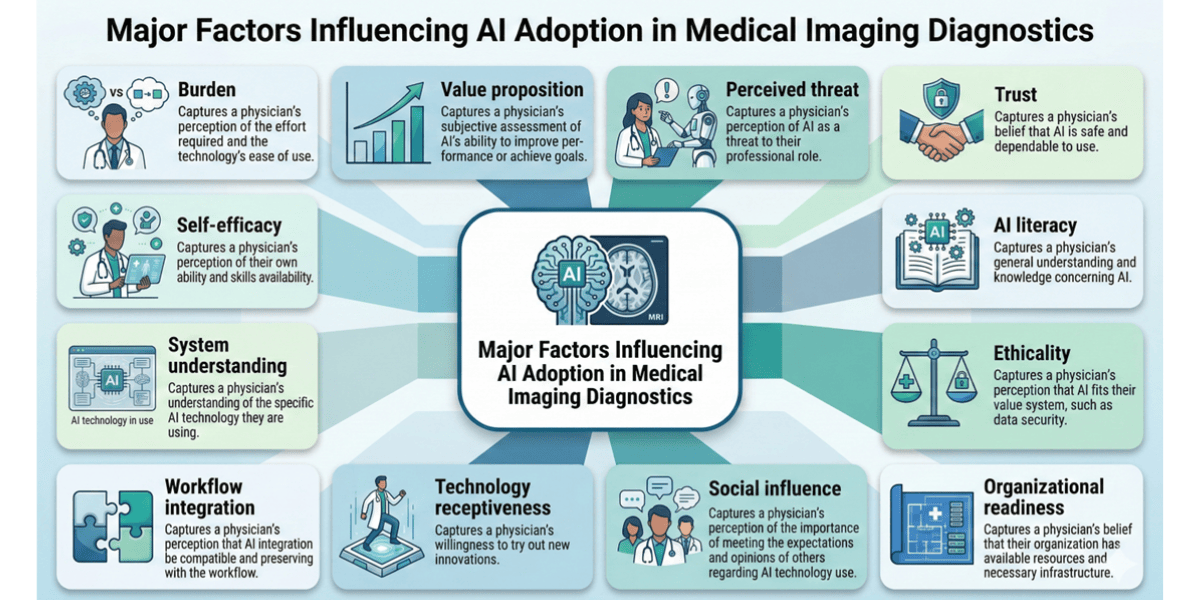
For hospitals and clinics, this research suggests that general-purpose AI did not, on average, lead to significant improvements in diagnostic quality or resource use. The takeaway isn’t to abandon AI, but to adopt it wisely. Instead of a full-scale rollout, a more prudent path involves starting with small-scale, measured, phased pilots followed by comprehensive evaluation and iterative improvement. Success lies not in the tool itself, but in deploying it in the right context, for the right people, in the right way, and with the right implementation process.
For healthcare professionals, AI tools could be seen as allies to support decision-making, but they are not as magic wands. Their greatest value lies in mitigating missed diagnoses and cognitive biases, not in making decisions for clinicians. It’s recommended to use these tools in high-uncertainty scenarios, compare your clinical assessment with the system’s suggestions, and document its limitations. Regular feedback to technical teams is crucial to enhance the tool’s safety and ensure your time is used effectively.
On a broader level, while this evidence shows AI isn’t replacing doctors, the underlying challenges, such as workforce shortages, uneven resource distribution, and rising costs, which remain very real. The core question is no longer whether to adopt AI, but how to do it wisely. The path forward requires avoiding blind faith in AI outputs, fostering continuous dialogue between clinicians and developers, and committing to learning in practice to integrate these digital tools into routine care effectively.
Figure. The study at a glance
References
[1] Hautz WE, Marcin T, Hautz SC*, et al.*Diagnoses supported by a computerised diagnostic decision support system versus conventional diagnoses in emergency patients (DDX-BRO): a multicentre, multiple-period, double-blind, cluster-randomised, crossover superiority trial. Lancet Digit Health 2025; 7(2): e136-e144
[https://doi.org/10.1016/S2589-7500(24)00250-4][PMID: 39890244]
[2] Kämmer JE, Hautz WE, KrummreyG*, et al.*Effects of interacting with a large language model compared with a human coach on the clinical diagnostic process and outcomes among fourth-year medical students: study protocol for a prospective, randomised experiment using patient vignettes. BMJ Open 2024; 14(7): e087469
[https://doi.org/10.1136/bmjopen-2024-087469][PMID: 39025818]
[3] Kunitomo K, Harada T, Watari T. Cognitive biases encountered by physicians in the emergency room. BMC Emerg Med 2022; 22(1): 148
[https://doi.org/10.1186/s12873-022-00708-3][PMID: 36028810]
[4] White AT, Vaughn VM, Petty LA*, et al.*Development of Patient Safety Measures to Identify Inappropriate Diagnosis of Common Infections. Clin Infect Dis 2024; 78(6): 1403–11
[https://doi.org/10.1093/cid/ciae044][PMID: 38298158]
[5] Aboueid S, Liu RH, Desta BN, Chaurasia A, Ebrahim S. The Use of Artificially Intelligent Self-Diagnosing Digital Platforms by the General Public: Scoping Review. JMIR Med Inform 2019; 7(2): e13445
[https://doi.org/10.2196/13445][PMID: 31042151]
[6] Nurek M, Kostopoulou O, Delaney BC, Esmail A. Reducing diagnostic errors in primary care. A systematic meta-review of computerized diagnostic decision support systems by the LINNEAUS collaboration on patient safety in primary care. Eur J Gen Pract 2015; 21 Suppl(sup1): 8–13
[https://doi.org/10.3109/13814788.2015.1043123][PMID: 26339829]
[7] Knitza J, Tascilar K, GruberE*, et al.*Accuracy and usability of a diagnostic decision support system in the diagnosis of three representative rheumatic diseases: a randomized controlled trial among medical students. Arthritis Res Ther 2021; 23(1): 233
[https://doi.org/10.1186/s13075-021-02616-6][PMID: 34488887]